
by top100admin | Sep 10, 2026 | AIMEDENT Journal Vol 1:4
The truth about COVID’s origins has now emerged: the very people who drove gain-of-function research that went catastrophically wrong were also the ones writing the rules for “protecting the public”—and lying at every turn. More than 7 million deaths, countless destroyed businesses, and an entire generation’s ruined education are the direct results of reckless, self-serving decisions by “Public Health” officials who prioritized their own power and personal financial interests over the public good. Not to mention the damaging societal changes that have left many people literally afraid to interact face-to-face, condemning them to lonely and solitary lives.
Who are these “Public Health” officials? Specialists in Public Health and Preventive Medicine are not typically recruited from the higher-performing students in a medical school class; the Public Health specialty has traditionally been less competitive than procedure-oriented or higher-income specialties such as dermatology, orthopedic surgery, and plastic surgery, and is often perceived by medical students as less prestigious or desirable, Those who self-select for this specialty are consigning themselves to careers spent working in institutional basements, navigating tedious red tape, wrestling with abstract mathematics, and combing through the literature for obscure trends.
Imagine these Public Health troglodytes being thrust suddenly into the limelight, fawned over by the media, and granted the power to control every facet of everyone’s life. Such power can have a narcotic effect. The COVID-19 pandemic, through the falsification of information, distortion of data, and suppression of significant scientific findings, helped concentrate control over entire countries into the hands of the very “Public Health” officials who had sworn to protect their populations. The resulting misery and suffering are well documented.
Would the public have been better served by an Augmented Intelligence–directed Public Health Authority? AI has no political affiliation or agenda, seeks neither media attention nor professional honors, and has no interest in cultivating relationships with celebrities or pursuing personal enrichment. Assuming proper design and governance, it can apply scientific standards consistently, require research data to substantiate claims, and identify and reject assertions that are unsupported or undocumented. It can also analyze broad trends in real time and continuously incorporate relevant new evidence to generate updated recommendations aimed at improving public health outcomes.
Taken together, the vast body of knowledge required to understand and oversee public health, along with the current bureaucracy’s evident shortcomings in preventing and managing common diseases, including COVID-19 and influenza, makes the potential and necessity of Augmented Intelligence unmistakable. The crucial question, therefore, is not whether Augmented Intelligence should have a role in public health, but which functions genuinely require human input?
About the author
 Dr. Freedman is a founder and past president, American Academy of Cosmetic Dentistry, a co-founder, Canadian Academy for Esthetic Dentistry, Regent and Fellow, International Academy for Dental Facial Esthetics, and a Diplomate and Chair of the American Board of Aesthetic Dentistry. Adjunct Professor of Dental Medicine, Western University, Pomona, California. Author of 14 textbooks and > 1000 dental articles.
George Freedman BSc, DDS, FIADFE, DiplABD, FAACD, FASDA, FPFA on behalf of the Artificial Intelligence Journal of Medicine and Dentistry (AIMEDENT Journal) – georgefreedmandds@gmail.com
by top100admin | Sep 10, 2026 | AIMEDENT Journal Vol 1:4
What a live audit of my practice revealed about Isaac, Trust AI’s practice-management platform, operational leakage, and the future of AI-enabled dental workflows.
A modern dental PMS should do more than store charts, schedules, and ledgers. It should help the practice identify leakage, prioritize action, protect chair time, strengthen recare, and make the business side of dentistry more visible without disrupting patient care.
The fear of switching is real
For nearly 20 years, I have practiced dentistry through the same technology evolution many dentists have experienced: from off-the-shelf software to server-based systems, to cloud and internet-based workflows, and now toward AI-enabled operational platforms.
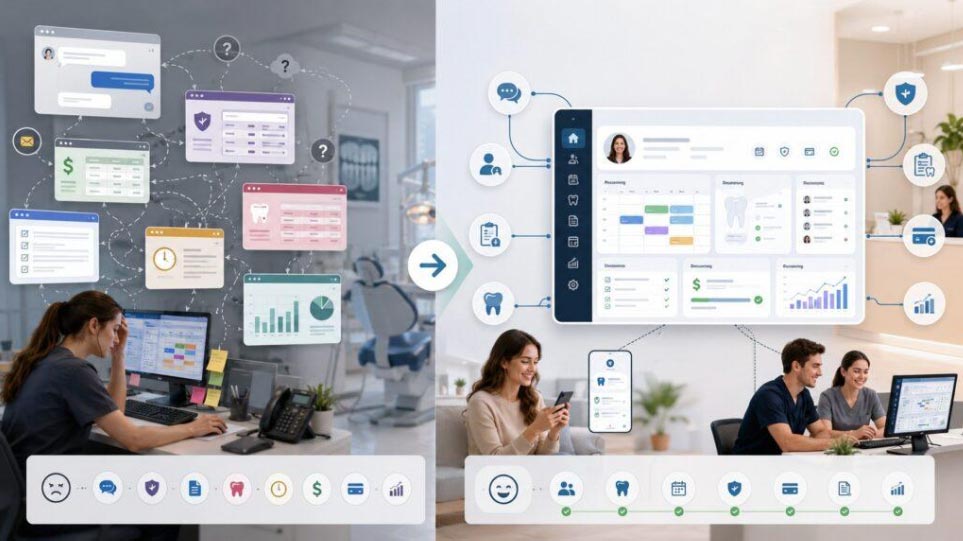
Each generation promised improvement. Some improvements were real, yet the practical burden on the dental office often remained familiar: multiple systems, multiple logins, fragmented workflows, recurring administrative workarounds, and the persistent concern that a major transition could disrupt patient care, billing, scheduling, claims, communication, or staff coordination.
That concern is rational. A dental office has very little room for operational instability. We cannot afford missed patients, broken schedules, lost data, interrupted billing, confused staff, or weeks of uncertainty. For that reason, many dentists tolerate outdated systems, high monthly software expense, and fragmented workflows because the idea of switching feels more dangerous than staying put.
Who we are, and why the decision mattered
I am the founder of Desert Dream Dentistry & Spa in Palm Desert, California. Our office is a comprehensive, high-technology, community-trusted dental practice with multiple dentists and specialists involved in patient care.
We provide care across general dentistry, cosmetic dentistry, implant dentistry, oral surgery, diagnostics, restorative care, and comprehensive treatment planning. Our patients expect consistency, access, communication, and clinical coordination at a high level.
That context matters. A practice like ours depends on operational continuity. The front desk, back office, clinical team, billing workflows, insurance coordination, treatment communication, scheduling, payments, follow-up, and patient experience all have to work together. When those systems do not communicate effectively, the cost is not merely financial. It becomes a staff burden, a patient-experience issue, and a management risk.

Desert Dream Dentistry & Spa in Palm Desert, California: a high-technology dental practice where clinical care, patient experience, and operational systems must work together without disruption.
What changed my view
My view began to change during our transition to Isaac, Trust AI’s AI-native practice-management platform. The most important factor was not only the software. It was the implementation experience itself.
Trust AI had a transition model that was materially different from what I expected. Our full integration and data transfer took approximately two weeks. During that period, business operations continued. Training occurred in parallel. The office remained functional. The team was supported. Most importantly, nothing was lost.
Instead of feeling like a disruptive PMS conversion, the transition felt more like a carefully managed operational upgrade. We continued seeing patients while the system was implemented, the data was transferred, and the staff was trained. That level of continuity matters because it removes one of the largest psychological and practical barriers dentists face when considering a platform change.
The economics of fragmentation are larger than subscription cost
The first economic question was simple: could a lower base subscription price and consolidated functionality reduce software overhead? That question mattered, and it still matters. Modern dental offices often operate with a patchwork of subscriptions: one system for the PMS, another for communication, another for insurance breakdowns, another for claims submission, another for forms, another for payments, another for analytics, and another for patient engagement.
A lower base cost is useful only if it is paired with operational value. In our case, the approximately $299 monthly base price, combined with consolidated functionality and visibility we did not previously have in one place, made the decision more compelling.
But the audit changed the conversation. It showed that the larger economic issue was not only what we were paying for software. It was what fragmented systems had failed to surface inside the practice: diagnosed treatment not scheduled, recare not configured, patients not reappointed, balances not separated into actionable and non-actionable categories, and cancellations not treated as an operational risk category.
What the audit revealed in our own practice
After migration, we ran a practice performance audit against our own data for the past approximately 10 years. This is where the analysis moved from anticipated savings to practice-specific findings. The audit was not a generic sales model. It was a baseline review of our own production, scheduling, recare, treatment planning, patient-pay collections, and data-quality issues.
With appropriate limitations understood, the findings were material. On a trailing-12-month production base of approximately $1.91 million, the audit identified roughly $1.0 to $1.3 million per year of recoverable or at-risk production in areas we were not actively working in a systematic way.
The largest category was unscheduled treatment. The audit identified approximately $2,156,282 in planned treatment across 674 patients and 4,170 procedures that had been diagnosed and treatment-planned but not scheduled or completed. Implant services alone represented $846,735 across 951 procedures, roughly 39% of the backlog. Restorative care, fixed prosthodontics, endodontics, oral surgery, and other categories made up the balance.
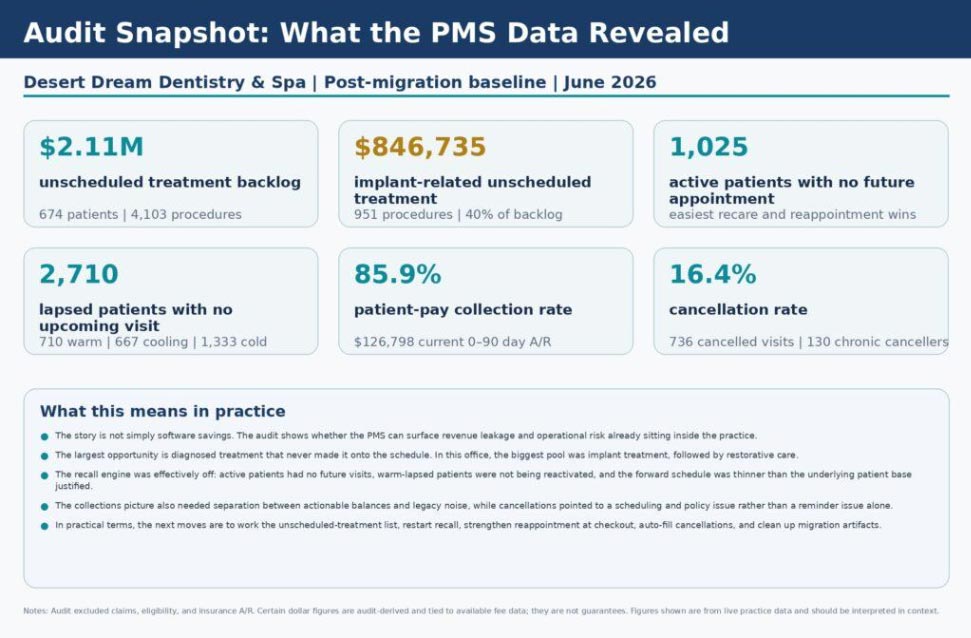
Audit-derived findings from Desert Dream Dentistry & Spa, shown as aggregate operational categories rather than patient-level details.
The schedule was telling us something
The audit also made the schedule easier to understand. We had 1,025 active patients who had been seen within 18 months but had no future appointment. We also had 2,710 lapsed patients with no upcoming visit: 710 warm patients last seen within 6 to 18 months, 667 cooling patients last seen within 18 to 36 months, and 1,333 cold patients last seen more than 36 months earlier.
At the same time, recall tracking was not configured. That is a critical finding because recall is one of the most basic engines of practice continuity. If recall is not properly configured and patients are not consistently reappointed before leaving, the schedule becomes dependent on human memory, manual effort, and reactive outreach.
The forward schedule confirmed the concern. The audit found 543 future appointments across 499 patients, with 141 appointments in the next 30 days. For a practice that had seen 1,190 patients in the prior year, that suggested the schedule was underfilled relative to the demand already present in the chart.
Collections and cancellations were also workflow problems
Collections were another example of why the PMS conversation cannot be limited to charts and schedules. The audit showed trailing-12-month production of $1,907,129 and collections of $1,638,528, which represented an 85.9% patient-pay collection rate. It also identified approximately $126,798 in current 0-90 day A/R that was actionable now.
The audit was careful not to overstate the A/R picture. Total patient A/R appeared to exceed $2 million, but 92% was more than 90 days old and much of it appeared to be legacy or migration artifact rather than immediately collectible money. That distinction is important. A modern system should not merely show a large number; it should help the practice separate actionable balances from data noise.
Cancellations added another layer. The audit showed a 16.4% cancellation rate over the prior 12 months, with 736 cancelled visits out of approximately 4,487 booked visits. It also identified 130 chronic-cancellation patients. Reducing cancellations to a healthier range could free approximately 380 visit slots per year. That is not just a reporting issue. That is chair time, staffing efficiency, revenue continuity, and patient access.
Why this is different from a traditional PMS report
Traditional PMS reports can be useful, but in many practices they are difficult to run, difficult to interpret, and too disconnected from daily action. A report that sits in a menu does not change behavior. A dashboard that is not tied to team workflow does not automatically improve the schedule. A number that is not connected to outreach, recall, collections, or follow-up is still only a number.
What made the Isaac experience different was the way the audit converted practice data into specific action categories. It did not simply say that there was unscheduled treatment. It identified the size of the backlog, the patient pool, the procedure mix, and the categories of work that should be prioritized. It did not simply say recare was weak. It separated active-no-future patients from warm, cooling, and cold lapsed patients. It did not simply show A/R. It separated current actionable balances from likely legacy artifacts.
That is the meaningful shift: from a system of record to a system of action. A system of record stores what happened. A system of action helps the practice decide what should happen next. And once the practice gives the green light, the platform does not stop at the recommendation. It runs the work itself: personalized outreach to unscheduled and lapsed patients, recall configured and managed, and the backlog worked systematically. The practice decides what to pursue; the system carries it out.
How this should translate into the practice
For our office, the practical translation is straightforward. First, work the unscheduled-treatment backlog systematically, beginning with the highest-value diagnosed treatment and the patients most likely to proceed with care. Second, restart the recare engine by configuring recall and segmenting patients based on recency of contact. Third, improve the forward schedule by making reappointment before checkout a disciplined operating standard.
Fourth, address cancellations as a defined risk category rather than a daily annoyance. Chronic cancellers should be identified, confirmed differently, and, where appropriate, managed with deposits or policies that protect chair time. Fifth, clean the data. Migration artifacts, duplicate treatment plans, and questionable large balances must be reviewed so reports become more reliable over time.
One practical change was immediate: our front office and clinical team began asking Isaac more targeted questions each day, using the audit to identify patients with unscheduled treatment, no future appointment, or recall gaps. Instead of waiting for a report to be pulled at month-end, the staff now locates those patient groups in Isaac, verifies what is actionable, and follows up in a more organized way. That has changed the daily workflow from passive reporting to active patient-specific outreach.
Those steps are not glamorous, but they are exactly where dental practices often win or lose profitability. The technology matters because it can make these loops visible and repeatable. The doctor and team still have to lead the process, but the system should make the right work easier to find and easier to act on.
What dentists should take from this
I would not present my practice audit as a universal promise for every office. Every practice has different contracts, patient volume, staffing, payer mix, clinical mix, fee schedule, data quality, and operational discipline. Dentists should be skeptical of any technology claim that sounds automatic or guaranteed.
But I would strongly encourage dentists to ask a different question of their practice-management systems. The question is no longer only, “Can this software store my schedule, chart, ledger, and claims?” The better question is: “Can this platform help me see what my practice is missing, prioritize what is actionable, and support my team in closing the loop?”
That is where Isaac changed my thinking. It was not merely the transition. It was not merely a lower base cost. It was not merely the possibility of reducing software subscriptions. It was the combination of implementation support, consolidated functionality, AI-enabled visibility, and practice-specific action intelligence.
A call for due diligence, not blind adoption
This article is not intended as a blanket recommendation that every dentist immediately change systems. Every office should conduct its own due diligence. Dentists should carefully review data-migration protocols, cybersecurity and HIPAA-related safeguards, support commitments, contract terms, integration options, billing implications, claims workflows, staff-training plans, reporting capabilities, AI-related functions, and exit rights before making any transition.
But dentists should also stop treating fear as a substitute for analysis. The old world of dental software made switching feel dangerous. A better implementation model, a more connected platform, and a serious audit of what is already happening inside the practice can make the decision far more rational.
For my practice, Isaac became more than a PMS replacement. It became a foundation for a different way of looking at dental operations. The next frontier is not simply replacing one software vendor with another. It is building a modern dental operating environment around the practice: the PMS as the backbone, supported by intelligent workflows that improve patient experience, front-office coordination, clinical communication, administrative visibility, revenue recovery, and doctor oversight.
Practice-specific findings used in this article
| Audit category |
Practice-specific finding |
| Trailing-12-month production base |
~$1,907,129 (~$159K/month) |
| Unscheduled treatment backlog |
$2,156,282 across 674 patients and 4,170 procedures |
| Implant-related unscheduled treatment |
$846,735 across 951 procedures |
| Active patients with no future appointment |
1,025 |
| Lapsed patients with no upcoming visit |
2,710 total: 710 warm, 667 cooling, 1,333 cold |
| Forward schedule |
543 future appointments across 499 patients; 141 in next 30 days |
| Patient-pay collection rate |
85.9%; current actionable 0-90 day A/R approximately $126,798 |
| Cancellation rate |
16.4%; 736 cancelled visits; 130 chronic-cancellation patients |
About the author
 Dr. Kianor Shah, DMD, MBA, is a practicing dentist, inventor, and healthcare entrepreneur based in Palm Desert, California. He is the founder of Desert Dream Dentistry & Spa and Global Summits Institute. His work focuses on clinical dentistry, healthcare innovation, practice operations, and doctor-to-doctor collaboration.
by top100admin | Sep 10, 2026 | AIMEDENT Journal Vol 1:4
I am an oral and maxillofacial surgeon in Tirana, Albania. My clinic, DemiraqiDental, is a dental day hospital: six dental operatories, a facial aesthetics room, a surgical theatre, 3D CBCT imaging, a clinical laboratory, and blood-exam facilities. I am not an IT professional and have never worked in technology — yet over the past year, I built and now operate a fully local artificial intelligence system for this clinic, running entirely on hardware in the building, with no patient data ever leaving it. No IT department was involved, because there is none: one surgeon, evenings, and a workstation.
I am writing not to present results — those will follow in a formal publication — but to share four observations that I believe matter to any colleague considering AI in their practice.
First: the barrier is lower than advertised, but not where you expect it. The prevailing assumption is that clinical AI requires cloud subscriptions, vendors, and an IT department. It does not. Open-source language models, speech recognition, and retrieval systems can run on a workstation a clinic can afford — the decisive components being the graphics card and enough power supply, not the processors or memory that dominate enterprise pricing, needed but not mandatory. My most consequential hardware purchase was a refurbished gaming GPU. What the brochures never mention is where the real cost lives: time. Weeks of evenings spent debugging, learning, failing, and documenting. The technology is accessible; the patience is the investment.
Second: for those of us practicing outside the major languages, local AI is not a preference — it is often the only honest option. Albanian is a low-resource language. Commercial AI products are rarely evaluated in it, and their quality in it is rarely disclosed. Running models locally allowed me to test, in my own language, with my own clinical vocabulary, as a native speaker and specialist — and to reject what failed. The clinic’s assistant now answers patients’ questions about procedures, hours, and appointments in Albanian, over the messaging platform they already use, grounded in documents I wrote and reviewed myself. Every AI-generated clinical text in my practice remains a draft until a doctor has reviewed it. That rule is not negotiable, and I would urge it on every colleague.
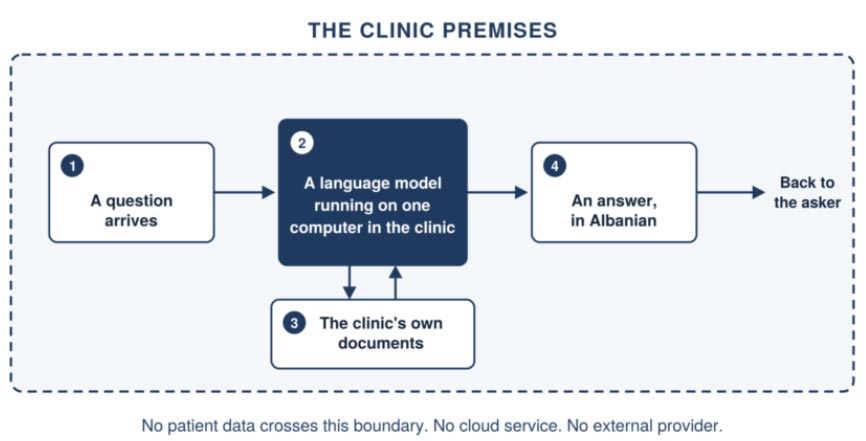
Clinic AI flow
Third: data sovereignty turned out to be the strongest argument, not the afterthought. Under European data-protection expectations, the simplest compliance posture a small practice can hold is also the most radical one: the data never leaves. No processing agreements with AI vendors, no transatlantic transfers, no wondering what a provider logs. For a private clinic without an IT department, “local” converts a legal question into an architectural fact.
Fourth: working safely with AI as a non-programmer required inventing rules — and writing everything down. Early on, every session with an AI assistant started from zero: screenshots, photographs of screens, re-explaining the whole system. Over time this evolved into a discipline: a versioned file of permanent working rules (evidence before conclusions; every command labeled as read-only or system-changing; one step at a time, verified), and a short, structured summary written at the end of each working session that the next session reads first. The effect was dramatic — hours of re-explanation collapsed into minutes, and mistakes stopped repeating. The rules themselves evolved the way clinical protocols do: each failure produced a written amendment. I now believe this documentation habit, not any particular software, is what makes AI genuinely usable by a clinician working without technical staff.
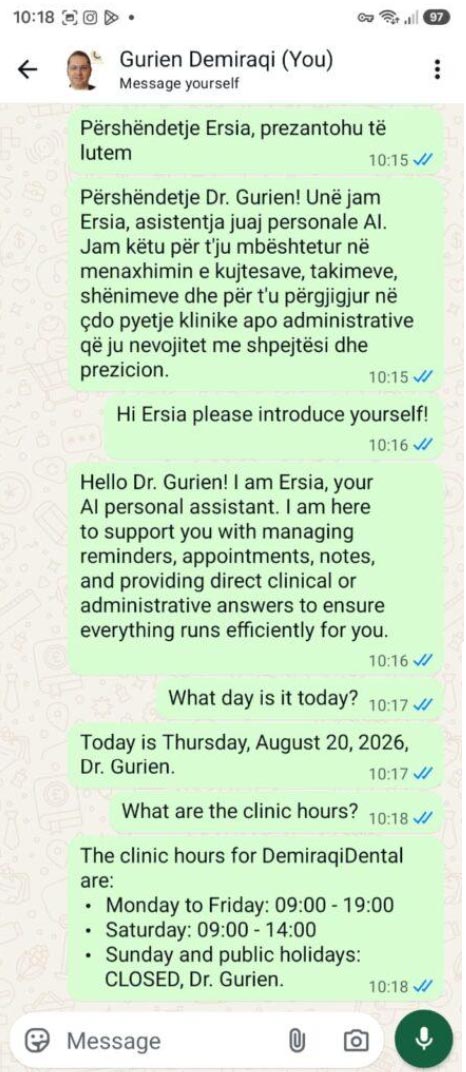 I went into this with larger dreams — digital avatars presenting in Albanian, ambient clinical documentation, an AI greeter at the front desk. A year ago, these sounded like fantasy for a private clinic without an IT department; today, the avatar pipeline works end-to-end on my own hardware, and the front-desk touchscreen is reality. What runs in production now — a private assistant that speaks my patients’ language, on my infrastructure, on my terms — turned out to be only the beginning.
A detailed technical and methodological account — hardware, costs, failures included, and the governance rules I developed to work safely with AI agents as a non-programmer — is in preparation for submission to an indexed journal. I share this letter in the meantime because I suspect there are many clinicians like me: curious, unfunded, and told that this is not for them. It is.
One final disclosure, offered with a smile: this letter itself was drafted in collaboration with one of the frontier AI assistants — the same class of agentic tools that built the clinic’s system with me. It seemed only fair to let the subject of the story help write it.
About the author
 Dr. Gurien Demiraqi is Professor and Head, Oral-Maxillofacial Surgery, Faculty of Med Sciences, Albanian University, Visiting Professor, Universal School of Health, University of California Albanian President, International Academy of Implantoprosthesis and Osteoconnection (IAIO). He is the Inventor, Sticky Tooth grafting material and co-inventor of the Baruti-Demiraqi approach Awarded.
by top100admin | Sep 10, 2026 | AIMEDENT Journal Vol 1:4
Every dentist knows the feeling: staring at a bitewing, squinting at a shadow, wondering is that early caries, or just an artifact? For decades, radiograph interpretation has relied entirely on the human eye. But today, artificial intelligence is stepping in as a powerful second set of eyes, helping dental teams detect what might otherwise be missed.
The diagnostic challenge
Studies consistently show that up to one-third of dental pathologies are difficult to detect visually on traditional X-rays. Subtle interproximal caries, early periapical changes, and fractures can evade even experienced clinicians — especially during a packed schedule when a dentist may review dozens of radiographs in a single day.
The consequences are real: missed findings lead to delayed treatment, more invasive procedures down the line, and erosion of patient trust. For insurance-driven practices, undocumented pathology also means lost revenue from claims that could have been substantiated.
How AI changes the game
Modern dental AI platforms analyze digital radiographs — bitewings, periapicals, and panoramic images — in seconds. Using deep learning algorithms trained on millions of annotated images, these systems highlight areas of concern with remarkable precision.
VELMENI is a modern dental AI software that helps analyze bitewing, periapical, panoramic as well as CBCT X-rays and instantly provides analysis through its robust AI models.
Let’s talk about the CHALLENGES faced in a dental office and how AI helps the dental team.
Challenge 1: Reducing missed diagnoses in high-volume dental practices
In a busy dental practice, early or incipient caries can be difficult to detect on radiographs, increasing the risk of missed diagnoses. Even when dentists identify these lesions, explaining subtle findings on traditional black-and-gray X-rays can be challenging.
From the patient’s perspective, understanding radiographs is often difficult. Dentists may spend 20–30 minutes explaining findings, yet patients may still struggle to visualize the problem, leading to delayed treatment acceptance.
The AI solution
For dentists:
VELMENI’s AI analyzes radiographs within seconds as soon as they are captured in an imaging software and highlights potential areas of concern, such as incipient caries, providing a reliable second set of eyes and improving diagnostic confidence (Figure 1).
For patients:
VELMENI visually highlights dental conditions directly on the X-ray, making findings easier to understand. This improves patient education, reduces consultation time, and helps patients make treatment decisions with greater confidence.
Fig. 1
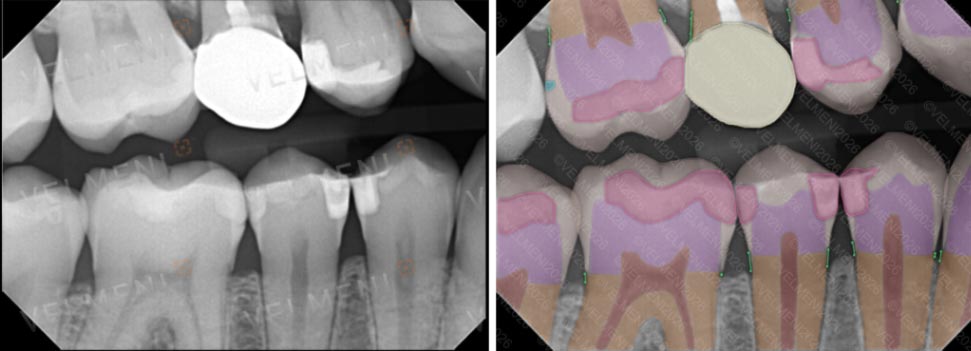
VELMENI’s AI radiographic prediction in Figure 1:
- Detected incipient caries on #3 as a blue color visual that can be missed by the human eye.
- # 3,5,28,29,30,31 – Filling/restoration predicted in pink.
- Bone level measurements <2mm highlighted in green color.
VELMENI’s client views:
After implementing VELMENI at Beaches Dentistry, Dr. Nodesh observed:
- 20% increase in case acceptance
- 6% revenue uplift
Challenge 2: Maintaining patient trust over time
During COVID, I was shadowing a dentist in New Jersey when a patient walked into the office visibly upset.
“Hey Dr. Shah, I visit you twice a year. Why didn’t you tell me I had a cavity during my last visit?”
The dentist had done everything correctly. The cavity simply wasn’t present — or wasn’t detectable — during the patient’s previous appointment. Yet the challenge wasn’t the diagnosis; it was rebuilding the patient’s trust.
The dentist had to pull up past records, compare X-rays, explain the progression of the condition, and reassure the patient that nothing had been missed. What should have been a straightforward conversation turned into a lengthy discussion.
The AI solution: Side-by-side comparison of current and historical radiographs
VELMENI enables side-by-side comparison of current and historical radiographs, automatically highlighting new findings and changes over time.
For dentists, this means spending less time searching through records and more time focusing on patient care. For patients, the visual comparison clearly demonstrates what has changed since their last visit, helping them understand why a condition may not have been present or visible before.
The result is faster conversations, improved transparency, and stronger patient trust — all within minutes.
Beyond 2D: The 3D frontier
Challenge 3: CBCT quality assurance
CBCT scans generate hundreds of image slices, making them time-consuming to review.
As a prosthodontist, I interpret CBCTs only as needed for my specialty — a challenge shared by many general dentists and specialists. Unlike oral radiologists, most clinicians are not trained to identify every artifact or scan-quality issue.
As a result, there is often uncertainty about whether a scan is diagnostically correct or whether a retake is needed. Recalling a patient for another CBCT means additional inconvenience, delays, and unnecessary radiation exposure.
The AI solution
VELMENI’s AI reviews CBCT scans within minutes and automatically identifies quality issues, artifacts, and potential retake requirements while the patient is still in the chair.
This enables dentists to make immediate decisions, avoid unnecessary patient recalls, reduce workflow disruptions, and ensure that every CBCT scan is clinically usable from the start.
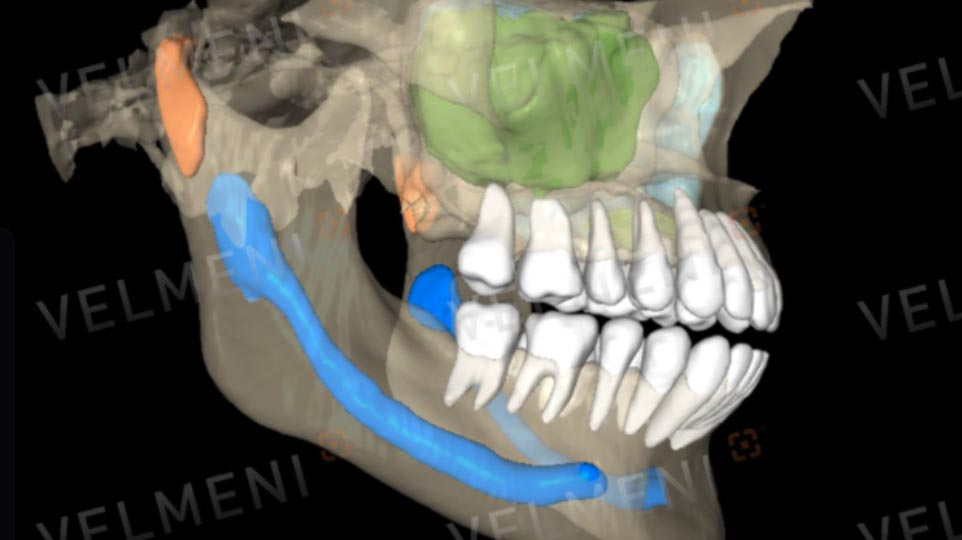
Also, colour coded visuals in a CBCT helps a dentist to explain to the patients about conditions like sinus pathology or a sinus lift required during implant cases (Figure 2).
Fig. 2
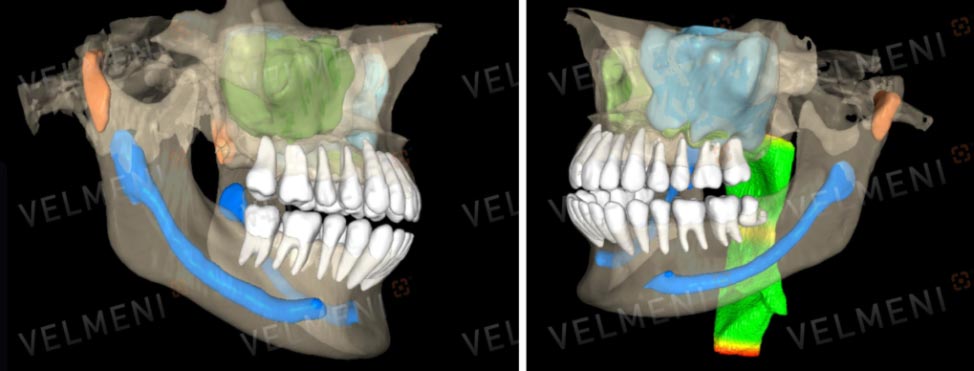
VELMENI’s AI analyzes:
- Mandibular canal in blue.
- Green color sinus highlights pathology in the sinus, thus helping the dentists explain the proximity of the tooth to the sinus.
- Blue color sinus indicates a healthy sinus.
- AI also annotated the airways and can also predict volumes in different areas.
The human element remains central
It’s important to emphasize: AI does not replace the dentist. Every finding flagged by the algorithm is reviewed, accepted, or rejected by the clinician. The dentist remains the decision-maker. AI simply ensures that nothing slips through the cracks, giving practitioners the confidence that their diagnoses are thorough and well-supported.
As dental AI becomes more widely adopted — already present in over 500 practices across 50+ countries — we’re witnessing a shift toward proactive, precision-driven care. Dentists who embrace these tools aren’t just improving their diagnostic accuracy; they’re elevating the patient experience and future-proofing their practices.
The era of squinting at shadows is ending. With AI by their side, dentists can see more, catch more, and do more — all while keeping patients smiling.
About the authors
 Dr. Alan Friedel, Chief Dental Officer Velmeni Inc., Clinical Program Director, Florida Institute for Advanced Dental Education, Dental Coding Consultant Faculty, Florida Institute for Advanced Dental Education.
 Dr. Vidhi Shah is a prosthodontist with a master’s degree in information technology and a Business Analyst at VELMENI. She is passionate about combining dentistry and technology to improve clinical workflows and advance innovation in the dental industry.

by top100admin | Sep 10, 2026 | AIMEDENT Journal Vol 1:4
The brain doesn’t resist AI. It resists uncertainty.
Every time I speak about AI, someone inevitably says, “People are resistant to change.”
I always smile because I don’t believe that’s true.
Human beings aren’t wired to resist change. We adapt every day. We upgrade our phones, learn new software, change jobs, move across the country, and reinvent ourselves more often than we realize.
What our brains resist is uncertainty.
The moment we can’t predict what’s coming next, our nervous system begins scanning for danger instead of possibility. That’s not a character flaw. It’s neuroscience.
Understanding that distinction changes everything about how we lead.
As artificial intelligence reshapes healthcare at an unprecedented pace, organizations are investing millions in technology, training, and implementation. Yet many of those initiatives stall for one simple reason. Leaders focus on teaching people how to use AI before helping them understand how to navigate the uncertainty it creates.
Technology isn’t the greatest challenge. The human brain is.
The brain is designed to keep us safe. It constantly predicts what will happen next based on previous experiences. When those predictions no longer work, whether because of a new technology, a changing workflow, or a rapidly evolving industry, the brain experiences what neuroscientists call a “prediction error.” The result is often hesitation, skepticism, or fear.
Those reactions aren’t signs that people are unwilling to learn. They’re signs that their nervous system is trying to restore certainty. Although uncertainty is also a human need, it can create a reaction that causes people to shrink from their own potential.
That’s why facts alone rarely change minds.
You can’t coach someone out of fear simply by giving them more information.
When uncertainty is high, the emotional centers of the brain become more active while the areas responsible for creativity, problem-solving, and sound decision-making become less available. Until people feel psychologically safe, they struggle to access the very thinking leaders are asking them to demonstrate.
This is where leadership changes everything.
I’ve come to believe that the future belongs to leaders who understand one simple truth:
Influence must come before innovation.
Technology may change overnight. Human trust does not.
That’s why I use what I call the Influence Before Innovation Model, a simple framework for helping people move through uncertainty with confidence instead of fear.
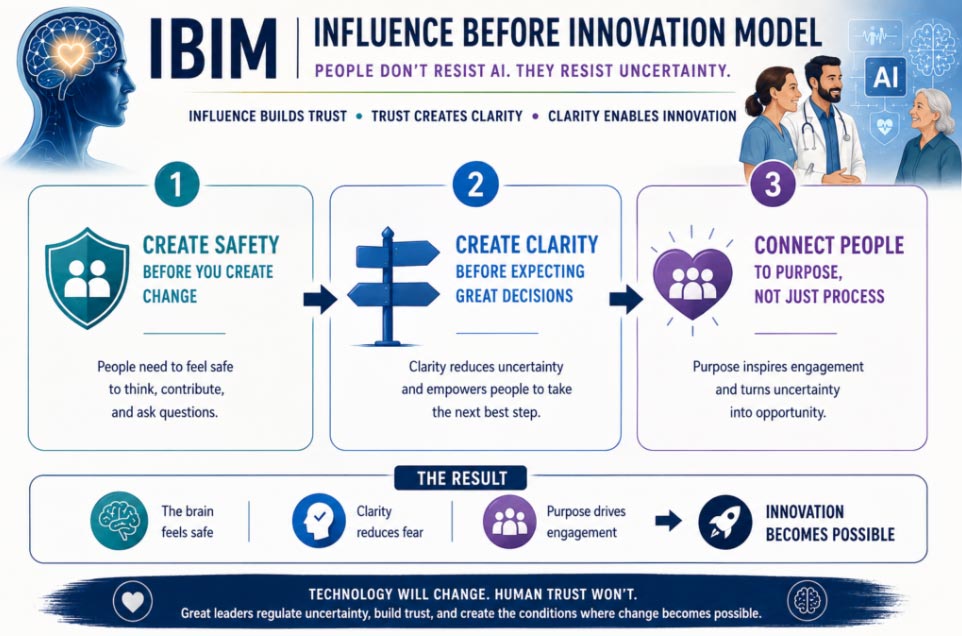
Influence Before Innovation Model
- Create safety before you create changePeople don’t perform at their best when they feel threatened. They perform at their best when they feel safe enough to think, contribute, and ask questions.Psychological safety doesn’t mean lowering expectations. It means creating an environment where learning is valued more than appearing perfect.
Leaders often underestimate the power of saying, “We’re learning this together.” That simple shift transforms uncertainty from something to survive into something to explore. When people stop protecting themselves, they start engaging.
- Create clarity before expecting great decisionsThe brain loves certainty because certainty conserves energy.When expectations are unclear, people naturally default to old habits. Not because they’re unwilling to change, but because familiarity feels safer than ambiguity.
Great leaders reduce unnecessary cognitive overload by answering three simple questions:
- Why does this matter?
- What does success look like?
- What is the next best step?
People don’t need every answer before moving forward. They simply need enough clarity and simple systems to take the next step with confidence. This means creating conditions for people to be able to move forward easily in the moments they are expected to make decisions.
Progress creates confidence far more effectively than perfection.
- Connect people to purpose, not just processAI is a remarkable tool, but people aren’t inspired by tools. They’re inspired by meaning.Healthcare has always been rooted in human connection. AI should strengthen that mission, not replace it. When leaders focus exclusively on software, workflows, and efficiency, they unintentionally create emotional distance. When they remind people that technology gives them more time to think, connect, care, and solve meaningful problems, everything changes.
Purpose quiets fear because it gives uncertainty somewhere to go. People willingly embrace change when they understand the greater impact of that change.
The organizations that will thrive in the AI era won’t necessarily have the most advanced technology. They’ll have leaders who know how to regulate uncertainty before trying to manage performance. They’ll recognize that influence isn’t about convincing people to change. It’s about creating the conditions where change becomes possible. That’s a profoundly human skill.
AI will continue to become faster, smarter, and more capable. The real competitive advantage won’t be artificial intelligence. It will be emotional intelligence, differentiation, and ease of adoption. It will be leaders who understand how the brain responds to uncertainty and who know how to transform fear into curiosity, confusion into clarity, and resistance into momentum.
The future of healthcare will absolutely be shaped by technology. But it will be led by people.
People who know how to build trust. People who know how to create certainty without pretending to have every answer. People who understand that the most advanced technology in the world will never replace a leader who can inspire confidence, cultivate resilience, and bring out the very best in others.
Because in the end, the brain doesn’t resist AI. It resists uncertainty.
And that’s exactly where great leadership begins.
About the author
 Julieanne O’Connor is a TEDx Speaker and neuroscience-based leadership strategist who partners with physicians, dentists, healthcare executives, and organizations to accelerate leadership, strengthen team performance, and guide successful transformation through human-centered influence.
